Obstetrics
The intended route of delivery is agreed with you before term, with the reasons stated in writing.
Delivery and VBAC in Hyderabad
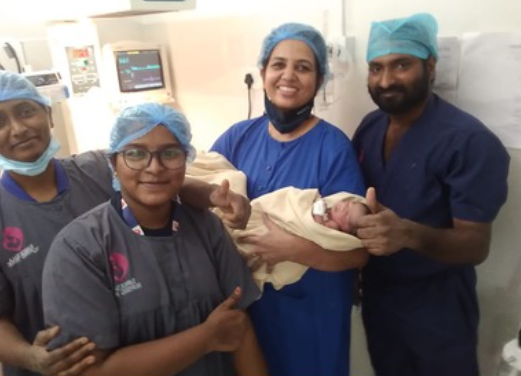
How your baby is born should be a decision made with you before labour starts, not one made for you in the middle of it. Dr. Sradhanjali discusses the intended route of delivery well before term, records the reasons, and is present for the delivery at a partner hospital. Normal vaginal delivery is the default wherever it is safe; caesarean is done on a stated indication.
A written plan removes the two commonest sources of distress at delivery: not knowing what will happen, and decisions taken in a hurry by someone who does not know your pregnancy. With one doctor from the first visit to the birth, the plan reflects your whole history.
Supported labour with continuous monitoring, induction only where indicated, and intervention when there is a clear reason — not for convenience.
Elective or emergency caesarean is offered where the indication is clear — placenta previa, breech at term, foetal distress, or a previous uterine scar that makes labour unsafe.
An epidural gives effective pain relief in labour while you remain awake and able to push. It is offered at the partner hospital by an anaesthetist and does not, in itself, increase the caesarean rate.
Most women in established labour. It is discussed at the 36-week visit so the decision is not made for the first time in pain.
A fine catheter placed in the back; relief within 15–20 minutes; monitoring of you and the baby throughout; topped up as labour progresses.
One previous caesarean does not automatically mean another. Where the criteria are met, a trial of labour is offered with the safeguards it requires.
A single previous low transverse caesarean, no other uterine surgery, a baby that is head-down and of normal size, and delivery in a hospital that can do an emergency caesarean quickly.
Continuous foetal monitoring, an anaesthetist and theatre available, and a low threshold to convert if labour does not progress or the trace changes.
In summary
Admission and delivery take place at nearby corporate hospitals where Dr. Sradhanjali is a visiting consultant. She remains your treating doctor there — the plan made at Sradha Women Care is the plan carried out on the day.
If any of these apply, book a visit rather than waiting for the next routine check.
Antenatal care from the first missed period to delivery, with the visit schedule set to your own risk profile.
Pregnancies that need closer surveillance, with defined thresholds for review and admission rather than reassurance alone.
Both partners assessed before you start trying, so problems are found before the pregnancy rather than during it.